Herpes Simplex (Oral & Genital)
Written 1st March 2020 - Last Update 30th August 2026
Herpes Simplex (Oral & Genital)
Condition
HSV-1 is mainly associated with oral/facial infection, HSV-2 with genital/ rectal infection (though either type can cause either site). After primary infection, HSV becomes latent in the dorsal root ganglia supplying the affected skin. Primary HSV-1 mainly occurs in infants/young children, especially in crowded/underdeveloped settings — nearly all children have been infected by age 5. Recurrences can be triggered by minor trauma, URTI, sun exposure, hormonal factors, or emotional stress (often no clear trigger). Itching/burning precedes an irregular cluster of small, closely-grouped, often umbilicated vesicles on a red base by an hour or two.
Oral HSV
Primary infection can present as gingivostomatitis: fever, restlessness, excessive dribbling, painful eating/drinking, foul breath, swollen/red/bleeding gums. Recurrences: painful lesions classically on the lips.
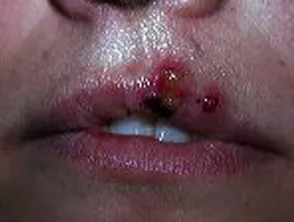
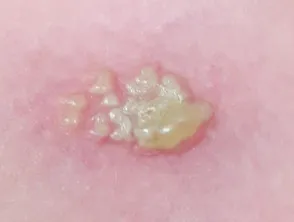
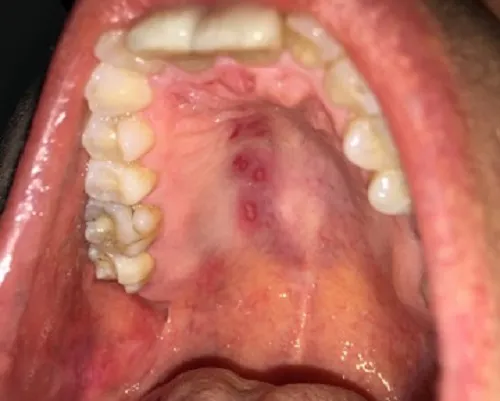
Management:
- Minor primary infection: supportive care, topical anaesthetic/analgesic (e.g. lidocaine 2% viscous, Difflam mouth rinse/spray).
- Severe primary infection: valaciclovir 1 g twice daily for 7 days.
- Minor recurrence: topical aciclovir 5% cream 5 times daily for 5 days, or famciclovir 1500 mg orally once.
- Severe recurrence (start within 48 hours): famciclovir 1.5 g once, or valaciclovir 2 g twice daily for 1 day.
- Long-term suppressive therapy: valaciclovir 500 mg daily for 6 months.
Genital HSV
A sexually transmitted infection; recurrent infections are usually caused by HSV-2. Painful genital ulcers, may start as vesicles, with redness and swelling lasting 2–3 weeks if untreated; often with fever and tender inguinal lymphadenopathy. Patients with undiagnosed HIV may present with unusually severe herpes initially. Consider an STI screen.
Management (antiviral therapy shortens the acute episode if started within 72 hours of symptom onset):
- First episode: valaciclovir 500 mg twice daily for 10 days (can stop at 5 days if response is rapid).
- Episodic therapy (start at prodrome): valaciclovir 500 mg twice daily for 3 days.
- Suppressive therapy (if several recurrences/year): valaciclovir 500 mg daily.
Investigations (both)
PCR of a viral swab from a fresh vesicle confirms the diagnosis.