Paediatric Vasculitis: Kawasaki Disease & IgA Vasculitis (HSP)
Written 9th November 2020 - Last Update 28th August 2026
Paediatric Vasculitis: Kawasaki Disease & IgA Vasculitis (HSP)
The two most common childhood vasculitides, covered together here.
Kawasaki Disease
Second most common childhood vasculitis (after IgA vasculitis/HSP, below). A clinical diagnosis. Early treatment with IVIg reduces morbidity and mortality.
- Demographics: 85% <5 years old; more common in children of Asian background.
Diagnostic criteria
Fever for ≥5 days AND 4 of the following 5:
- Conjunctivitis (bilateral, non-purulent)
- Cervical lymphadenopathy
- Rash — variable, but not vesicular or crusting; may be urticarial, morbilliform, or resemble scarlet fever
- Lip/oral mucosal involvement — redness/cracking of the lips, diffuse oropharyngeal erythema, strawberry tongue
- Extremity oedema/erythema progressing to desquamation, often with perineal desquamation
Children may not show all features — urgent paediatric review may be warranted with as few as 2 features present, given the consequences of a missed diagnosis.
Investigations
Echocardiogram at baseline, then at 6 weeks (coronary artery aneurysm surveillance).
Management
- IVIg 2 g/kg.
- High-dose aspirin until fever resolves (30–100 mg/kg/day in 4 divided doses), then low-dose aspirin (3–5 mg/kg daily) for 6 weeks if no coronary artery lesions are found.
- If coronary artery lesions are detected on echo, continue aspirin.
- Corticosteroids — controversial; used if fever persists after IVIg.
IgA Vasculitis (Henoch-Schönlein Purpura)
The most common vasculitis in children — can occur at any age.
Clinical features
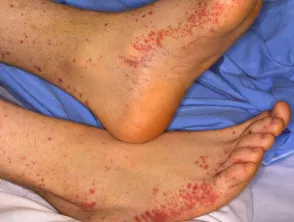
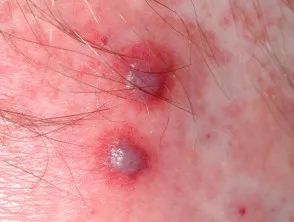
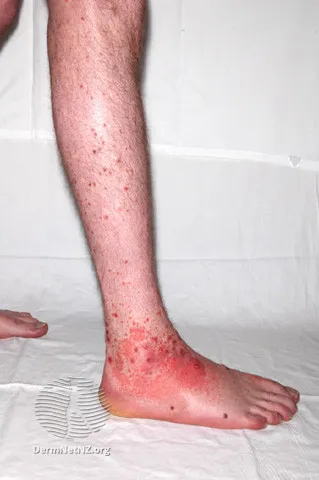
Palpable purpura over the lower limbs up to the buttocks; large-joint arthritis; abdominal pain. Typically follows a URTI, associated with strep throat — a post-streptococcal complication. Most recover within a few months.
Complications
May develop IgA nephritis. Other serious complications: GI haemorrhage (melaena), intussusception, scrotal involvement.
Treatment
Symptomatic. Monitor for renal involvement — UEC and early morning urine for protein.