Congenital Adrenal Hyperplasia
Written 25th June 2020 - Last Update 19th July 2026
Congenital Adrenal Hyperplasia
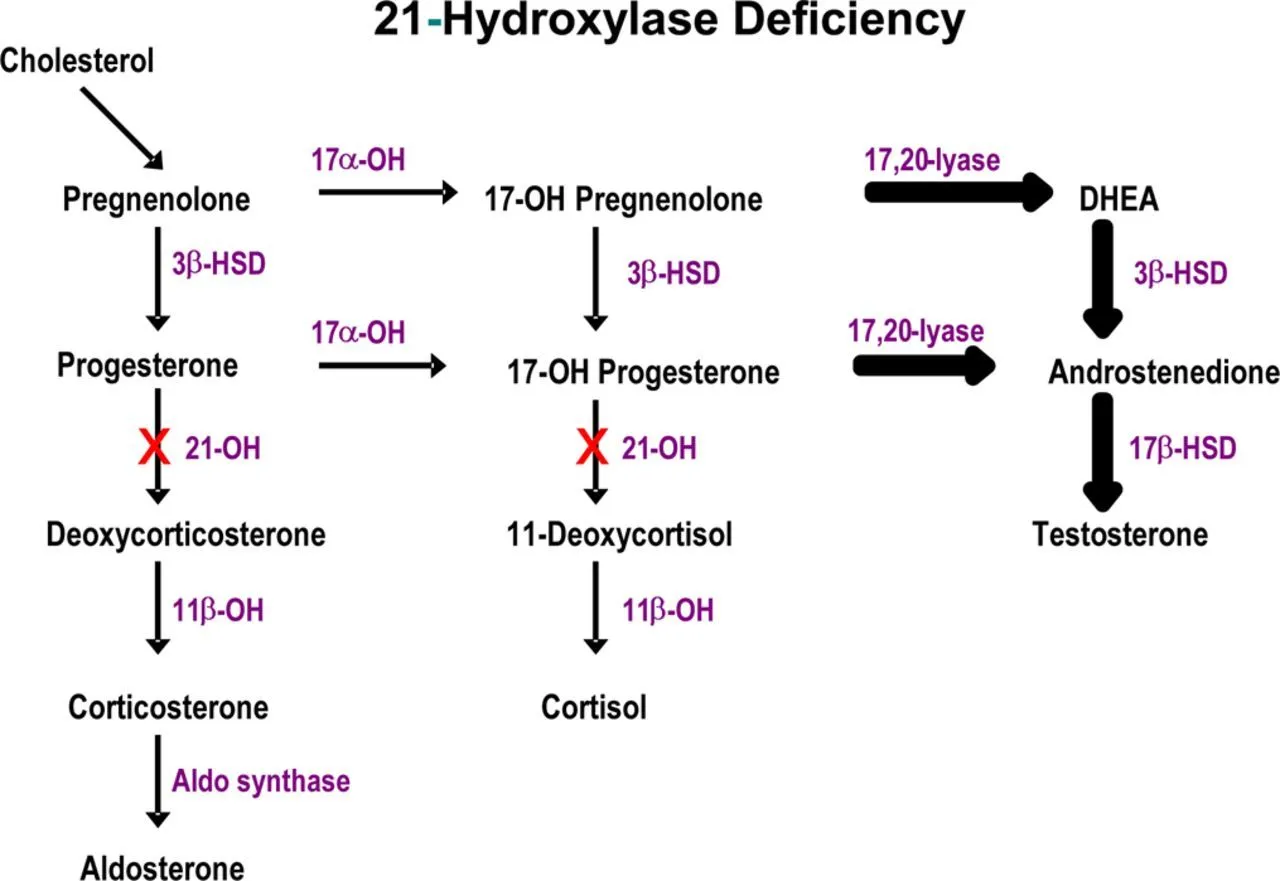
An autosomal recessive deficiency of an enzyme in aldosterone/cortisol synthesis — most commonly 21-hydroxylase deficiency. Reduced cortisol and aldosterone with a build-up of precursors shunted into androgens; loss of cortisol negative feedback raises ACTH (driving adrenal hyperplasia and further androgen excess).
Presentation
Usually in childhood.
- Females: neonatal virilisation of the external genitalia; sometimes pre-pubertal hirsutism.
- Either sex: infants may present with failure to thrive, vomiting and dehydration from a salt-losing crisis.
Investigation shows a raised 17-hydroxyprogesterone, with low cortisol and aldosterone.
Management
Specialist-managed. Lifelong glucocorticoid and mineralocorticoid replacement (e.g. hydrocortisone + fludrocortisone) — at higher doses than for simple adrenal insufficiency, because the goal is also to suppress ACTH-driven androgen excess.